

 with Dr. Dang Phuoc Dat at Family Hospital. Call/WhatsApp: +84919480180.)
Author & Medical Reviewer: Dr. Dang Phuoc Dat (Specialist Level I) – Urology, Andrology & Reconstructive Surgery, Family Hospital Da Nang | Updated: October 22, 2026
When conservative medical therapy fails to pass a urinary calculus, endoscopic kidney stone removal Da Nang encompasses four distinct minimally invasive procedures that have replaced over 95% of traditional open surgeries. Understanding how each endoscopic technique matches your stone’s exact location, millimeter size, and CT hardness empowers you to make an informed decision with your urologist.
Quick Clinical Summary: Modern endoscopic kidney stone removal relies on four targeted modalities: Semi-Rigid Ureteroscopy (URS) for distal/mid-ureteral stones; Flexible Ureteroscopy (RIRS) via the natural urinary tract for renal stones $\le 20\text{ mm}$; Mini-PCNL via a $5\text{ mm}$ flank tract for renal stones $> 20\text{ mm}$; and Retroperitoneal Laparoscopy for giant solitary extrarenal pelvic or ureteral stones. At Family Hospital Da Nang, Dr. Dang Phuoc Dat performs all four techniques.

1. The Four Pil>1. The Four Pillars of Endoscopic Kidney & Ureteral Stone Surgery
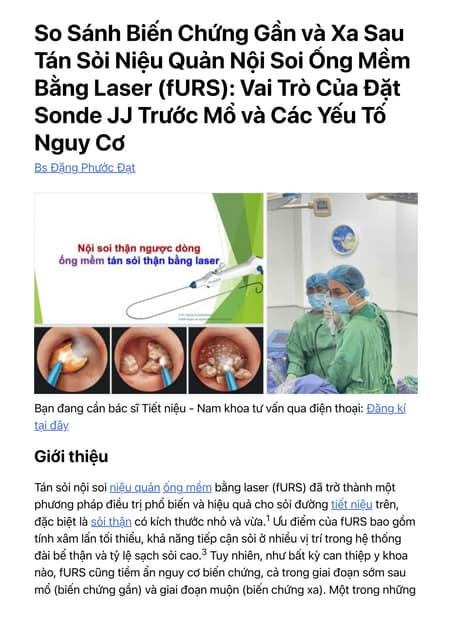
-block-paragraph">In contemporary urology, minimally invasive stone surgery is divided into Endourology (natural-orifice or miniature intrarenal lumina) and Retroperitoneal Laparoscopy:- Semi-Rigid Ureteroscopy (URS): Passes a slender endoscope through the urethra and bladder into the ureter to fragment distal and mid-ureteral stones with a Holmium laser.
- Retrograde Intrarenal Surgery (RIRS): Uses a steerable digital flexible ureteroscope to navigate into the upper ureter and renal calyces, dusting stones $< 20\text{ mm}$ with zero external incisions.
- Mini-Percutaneous Nephrolithotomy (Mini-PCNL): Establishes a $5\text{ mm}$ keyhole flank tunnel directly into the kidney to clear stones $> 20\text{ mm}$ or staghorn calculi.
- Retroperitoneal Laparoscopic Pyelolithotomy / Ureterolithotomy: Uses three small $5–10\text{ mm}$ retroperitoneal ports to extract an intact giant calculus ($> 25\text{ mm}$) from an extrarenal pelvis or upper ureter, followed by intracorporeal absorbable suturing.
EAU Clinical Deci>EAU Clinical Decision Matrix for Endoscopic Stone Surgery in Da Nang
"wp-block-table">| Stone Location & Size | First-Line Modality | Alternative Modality | Typical Hospital Stay |
|---|---|---|---|
| Renal Stone $< 10\text{ mm}$ (symptomatic) | Shockwave Lithotripsy (ESWL) or Flexible RIRS | Active surveillance if asymptomatic & non-obstructing | Day-case – 24 hours |
| Renal Stone $10 – 20\text{ mm}$ | Flexible Ureteroscopy (RIRS) or Mini-PCNL | ESWL (only if soft $< 1000\text{ HU}$ and favorable calyx) | 1 – 3 days |
| Renal Stone $> 20\text{ mm}$ / Staghorn | Ultrasound-Guided Mini-PCNL | Retroperitoneal Laparoscopy or staged RIRS | 3 – 4 days |
| Ureteral Stone $> 7\text{ mm}$ with Hydronephrosis | Semi-Rigid URS (distal/mid) or Flexible RIRS (proximal) | Mini-PCNL or Laparoscopic Ureterolithotomy (if $> 15\text{ mm}$ impacted) | 1 – 2 days |
2. Why Preoperative CT Urography Is Mandatory Before >2. Why Preoperative CT Urography Is Mandatory Before Endoscopic Stone Surgery
at Family Hospital Da Nang, Dr. Dang Phuoc Dat requires a non-contrast or contrast-enhanced CT Urography scan prior to scheduling any endoscopic stone removal:- Accurate 3D Stone Burden Measurement: Ultrasound acoustic shadowing frequently overestimates or underestimates stone size by 20–30%.
- Hounsfield Unit (HU) Hardness Profiling: Stones measuring $> 1000–1200\text{ HU}$ (such as Calcium Oxalate Monohydrate or Brushite) are resistant to external shockwaves and require high-power Holmium laser fibers.
- Anatomical Roadmap: Detects congenital anomalies such as horseshoe kidney, duplex collecting systems, or ureteropelvic junction obstruction (UPJO) prior to scope insertion.
3. Transparent Cost Structure for Endoscopic Stone Surger>3. Transparent Cost Structure for Endoscopic Stone Surgery in Da Nang
doscopic stone removal at Family Hospital Da Nang are itemized transparently across four components:- Preoperative Diagnostics & Anesthesia Workup: Complete blood count, coagulation profile, renal function (eGFR), urine culture, ECG, chest X-ray, and CT Urography.
- Surgical & Anesthesia Fees: Scaled according to technical complexity (semi-rigid URS is the most economical, followed by Mini-PCNL and digital flexible RIRS).
- Endourological Consumables: Holmium laser fiber, Nitinol extraction basket, ureteral access sheath (UAS), and internal Double-J Ureteral Stent.
- Inpatient Room & Medications: Optimized by short 1–4 day hospital stays and eligible for both Vietnamese BHYT and international health insurance direct billing.
Clinical Red Flags: When to Seek Immediate Urological Care<>Clinical Red Flags: When to Seek Immediate Urological Care
und-color:#fff5f5;border-left-color:#d32f2f;border-left-width:4px;padding-top:16px;padding-right:20px;padding-bottom:16px;padding-left:20px">URGENT MEDICAL RED FLAGS:
- Renal colic accompanied by fever (> 38.5°C), chills, cloudy foul-smelling urine, or hypotension: Definitive laser lithotripsy is strictly contraindicated during acute infected hydronephrosis; emergency decompression via Double-J stenting or percutaneous nephrostomy must be performed first.
- Persistent gross hematuria or inability to void after discharge warrants immediate review.